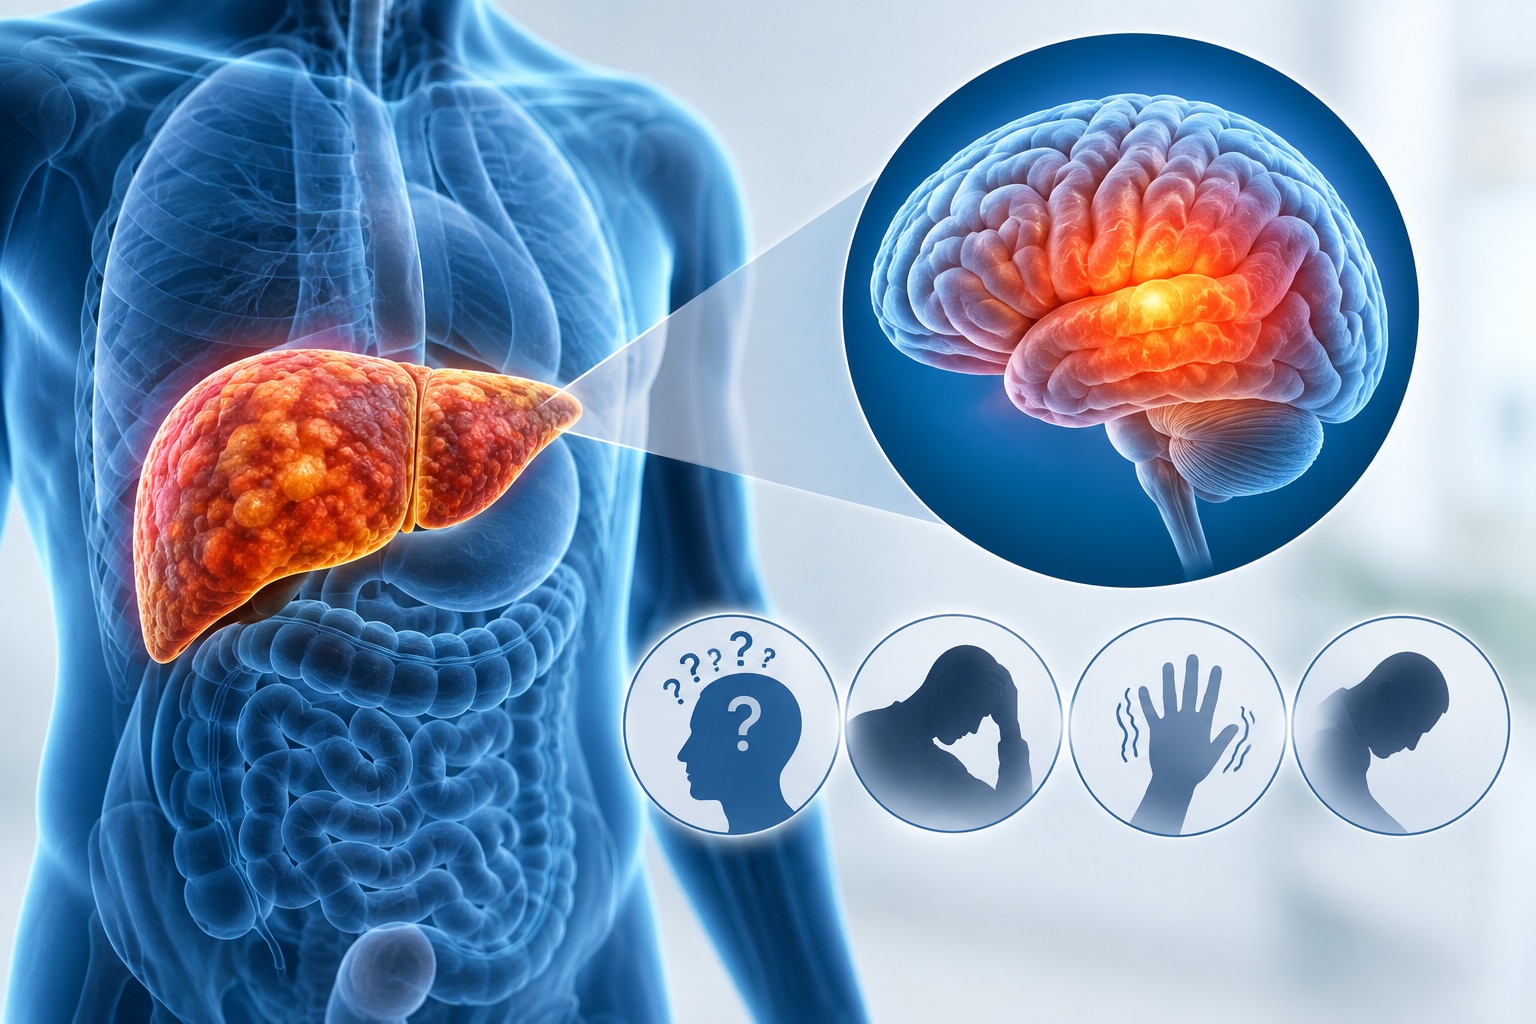
A person with liver disease can develop meaningful cognitive impairment while still holding a normal conversation, so waiting for obvious confusion delays care. You will learn how West Haven grades correspond to function, which warning signs demand emergency assessment, how clinicians rule out competing causes, and how treatment changes from an acute episode to recurrence prevention.
Key takeaways
- Grade 0 can hide attention and coordination problems despite normal conversation.
- Asterixis, sleep reversal, slowed responses, and personality changes need prompt review.
- Search for constipation, infection, bleeding, medicines, dehydration, and electrolyte disturbances.
- Recurrent or severe episodes warrant specialist review and possible transplant assessment.
How West Haven grades show progression from subtle impairment to coma
West Haven grades describe a functional decline, not just a change in medical terminology. Grade 0 can look normal in conversation, yet psychometric testing may reveal slowed attention or poor coordination. This is why early hepatic encephalopathy diagnosis cannot rely on a brief bedside chat alone.
| Grade | Everyday function | Typical classification |
|---|---|---|
| 0 | Appears normal; subtle errors in attention, memory or driving may emerge on testing | Covert or minimal HE |
| I | Sleep–wake reversal, shortened attention, anxiety or euphoria, slowed thinking and reduced work efficiency | Covert HE |
| II | Lethargy, irritability, personality change, inappropriate behaviour, time disorientation, slurred speech or asterixis | Overt HE in many studies; covert when disorientation is absent |
| III | Very drowsy, confused and grossly disoriented; struggles to follow commands and needs supervision | Overt HE |
| IV | Unresponsive coma; purposeful conversation and everyday function are impossible | Overt HE |
Covert HE means impairment is present without obvious confusion; someone may seem oriented but make calculation errors, write differently, lose words, or perform familiar tasks poorly. Overt HE is visible to others and can progress from abnormal behaviour to stupor or coma.
Asterixis supports toxic-metabolic encephalopathy but is not specific to HE, and it can disappear in deep coma. A clinician may add psychometric testing or a critical flicker frequency test; neither result alone proves or excludes HE.
Early warning signs that a routine conversation can miss
Early or covert HE often leaves conversation intact while slowing the tasks behind it. Watch for reversed sleep–wake patterns, reduced concentration, slowed thinking, difficulty finding words, new irritability or apathy, calculation mistakes, deteriorating handwriting, and poorer performance at work, home or while driving.
| Finding | What testing can reveal | What a routine conversation can miss |
|---|---|---|
| Psychometric testing | Errors in attention, processing speed, memory, visuomotor tasks or calculations | The person may answer questions coherently |
| Validated computerised testing | Subtle changes against age- and education-appropriate norms | Familiar conversation skills may remain normal |
| Critical flicker frequency testing | Difficulty recognising a rapidly flickering light as steady; a result around 39 Hz can support cognitive impairment | It cannot establish HE alone |
Psychometric testing should be administered and interpreted by trained clinicians, with examination and the clinical context. A critical flicker frequency test india search should lead you to a validated device and trained operator, not a home conclusion.
Vision, colour blindness, age, education, alcohol use and testing conditions affect the result; one low score does not prove HE, and a normal score does not exclude it.
Asterixis, seen as brief irregular lapses when the wrists are held out, strengthens concern for toxic-metabolic encephalopathy but is not specific to HE. Its absence does not rule out early disease. Share new driving errors, sleep reversal or handwriting change promptly, even if speech remains clear.
Why confusion requires a search for triggers and mimics
New confusion in a person with liver dysfunction or a portosystemic shunt is a diagnosis-of-exclusion problem, not proof of hepatic encephalopathy (HE) by itself. Even when cirrhosis symptoms are mild or absent, clinicians look for a reversible trigger and another explanation before settling treatment.
- Check for infection with temperature, examination, blood tests, urine testing and chest assessment. Sepsis can cause confusion without obvious local symptoms.
- Look for gastrointestinal bleeding, including vomiting blood, black stools, falling haemoglobin or blood in the digestive tract. Digested blood increases nitrogen load and can precipitate HE.
- Review bowel movements, fluid intake and medicines. Constipation, dehydration, kidney failure, sedatives, sleeping tablets, opioids and alcohol-related causes can all impair consciousness.
- Measure glucose and electrolytes, and assess sodium, potassium, kidney function and acid-base disturbance. Hypoglycaemia and metabolic abnormalities need different urgent treatment.
- Examine for a fall, head injury, stroke or other intracranial disease. Asterixis supports toxic-metabolic encephalopathy but also occurs in other metabolic disorders, so it cannot confirm HE.
A raised blood-ammonia concentration supports HE in the right clinical setting but does not establish it. A normal result makes clinically significant HE less likely and should prompt reassessment.
New disorientation, inability to stay awake, fever, severe abdominal pain, vomiting blood, black stools or a head injury requires emergency care; do not drive the affected person.
Treatment stages: correct the trigger, restore alertness and prevent recurrence
Acute treatment proceeds in three linked stages: correct the precipitant, restore alertness safely, then prevent another episode.
- Correct the trigger. New confusion, marked drowsiness, inability to follow commands, or reduced consciousness needs emergency hospital assessment. Clinicians search for causes such as infection, gastrointestinal bleeding, constipation, dehydration, or a sedating medicine while checking glucose, kidney function and electrolytes. Hospital care also protects the airway when swallowing or consciousness is impaired.
- Restore alertness. Lactulose is given in repeated doses until you pass about two soft stools, then adjusted to two or three soft stools daily. It is not a target to produce diarrhoea: excessive dosing can cause dehydration and electrolyte loss, worsening confusion. Never force oral medicine into someone who cannot swallow safely.
- Prevent recurrence. Rifaximin 550 mg twice daily is added to lactulose for recurrent overt episodes, particularly after a second episode. It does not replace trigger correction. Keep protein intake rather than restricting it: aim for about 1.2–1.5 g per kilogram of ideal body weight daily, spread across meals with a late-evening snack.
Vegetable and dairy proteins may be easier to tolerate, while prolonged restriction worsens muscle loss and ammonia clearance.
An ammonia result supports assessment but neither proves the diagnosis nor measures recovery reliably. A falling number does not excuse persistent confusion, and treatment response is judged by alertness, function and stool tolerance, not ammonia alone.
When specialist and transplant assessment becomes part of the plan
New confusion in a person with cirrhosis needs emergency assessment, not a routine appointment. Call emergency services or go to hospital if the person cannot stay awake, becomes disoriented, develops unusual behaviour, vomits blood, passes black stools, has fever, severe abdominal pain, or suffers a fall or head injury. Do not let them drive.
1. Move beyond routine follow-up after any decompensation: new or worsening ascites or leg swelling, jaundice, variceal bleeding, kidney deterioration, or overt HE. Recurrent overt HE, especially despite trigger control and prescribed prevention, warrants transplant-centre assessment.
2. Bring the complete medication list, including sleeping tablets, painkillers, opioids, supplements and recent antibiotics. Record the timing of confusion, bowel movements, fever, bleeding, alcohol use, falls and missed doses.
3. Prepare for continuing care: alcohol avoidance, nutrition and muscle-preservation planning, lactulose and rifaximin review, kidney and electrolyte monitoring, liver-cancer surveillance, and screening or surveillance for oesophageal varices.
Transplant evaluation does not mean surgery is immediate; it identifies risks, tests fitness, and allows timely planning before another crisis. Families seeking liver disease treatment in Mumbai should ask whether the service can arrange urgent hospital escalation, investigate HE triggers, and coordinate transplant assessment.
Dr Chetan Kalal Hepatologist Transplant can be part of that pathway when recurrent encephalopathy or other decompensation changes the treatment goal.
Frequently asked questions
What do West Haven grades show in hepatic encephalopathy?
They show functional decline from subtle attention and coordination problems at Grade 0 to disorientation, marked drowsiness, and coma at Grade 4.
Which early warning signs can a routine conversation miss?
Slowed attention, poor coordination, sleep reversal, personality change, handwriting difficulty, and asterixis can be missed during a brief conversation.
Why does confusion require a search for triggers and mimics?
Constipation, infection, gastrointestinal bleeding, dehydration, sedatives, kidney problems, and electrolyte disturbances can trigger encephalopathy or resemble it.
What are the treatment stages for hepatic encephalopathy?
Treatment identifies and corrects the trigger, restores alertness with prescribed therapy, and prevents recurrence through medication adherence, monitoring, and follow-up.
When should transplant assessment become part of the plan?
Repeated or severe encephalopathy, worsening cirrhosis, liver failure, or complications that persist despite treatment should prompt specialist and transplant assessment.
Keywords